
The Discovery of Penicillin and the Antibiotic Era
In 1928, Alexander Fleming's accidental discovery of penicillin in a contaminated petri dish launched a medical revolution. A decade later, Howard Florey, Ernst Chain, and the Oxford team transformed Fleming's observation into a usable drug, mass-produced it for Allied forces in World War II, and ushered in the golden age of antibiotics. The story extends into the global crisis of antimicrobial resistance, which threatens to undo the gains of the antibiotic era.
Events
Alexander Fleming Discovers Penicillin

Scottish physician Alexander Fleming returned from a summer holiday to his laboratory at St Mary's Hospital and found a petri dish of Staphylococcus aureus contaminated by a blue-green mould, later identified as Penicillium rubens. The mould had killed the bacteria immediately surrounding it while colonies farther away grew normally, indicating it secreted an antibacterial substance. Fleming named the substance "penicillin" and demonstrated that it could inhibit a range of Gram-positive bacteria, though he could not isolate or purify the compound himself. The accidental observation, aided by an unusual stretch of cool London weather that favoured the mould, laid the foundation for the antibiotic era.
Location: London, England
Fleming Publishes His Penicillin Findings
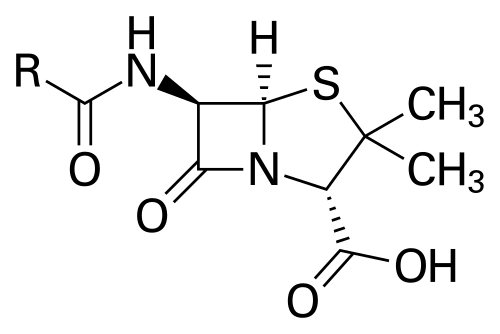
Fleming reported his findings to the British Journal of Experimental Pathology on 10 May 1929, with the paper appearing in the June 1929 issue under the title "On the Antibacterial Action of Cultures of a Penicillium." The article attracted little serious attention from the medical community, and Fleming himself was uncertain of penicillin's clinical potential, viewing it primarily as a useful tool for isolating bacteria in laboratory cultures. Unable to isolate the unstable compound and having lost his chemist collaborators to other positions, Fleming practically abandoned penicillin research by the end of 1929. The discovery would lie neglected for a decade until the Oxford team revived it.
Location: London, England
Florey and Chain Begin Penicillin Research at Oxford

In 1939, a multidisciplinary team at the Sir William Dunn School of Pathology, University of Oxford, led by Australian pharmacologist Howard Florey and including German-born biochemist Ernst Chain, began systematically investigating natural antibacterial agents. Their work led them to revisit Fleming's largely forgotten 1929 paper and a sample of penicillin mould that had been passed to the laboratory. The team — including Edward Abraham, Norman Heatley, Margaret Jennings, A. D. Gardner, and Jean Orr-Ewing — devised methods for cultivating the mould and extracting, purifying, and storing penicillin, and created an assay for measuring its purity. Chain's use of freeze-drying produced a dry, stable brown powder of active penicillin, overcoming a key obstacle to clinical use.
Location: Oxford, England
First Animal Test of Penicillin

On 25 May 1940, the Oxford team conducted a decisive animal experiment: eight mice were injected with a lethal dose of streptococcus, and four were then treated with penicillin. All four untreated mice died within a day, while all four treated mice survived, demonstrating penicillin's protective effect against systemic bacterial infection in a living animal. The results were published in The Lancet on 24 August 1940 in the paper "Penicillin as a Chemotherapeutic Agent," establishing for the first time that penicillin could cure infection in vivo. This proof-of-concept opened the door to human clinical trials.
Location: Oxford, England
First Human Clinical Trial of Penicillin
On 12 February 1941, the Oxford team administered penicillin to Albert Alexander, an Oxford police constable suffering from a severe streptococcal and staphylococcal infection, making him the first human treated with the purified drug. Alexander improved dramatically within days as the infection receded, but the team had produced so little penicillin that supplies ran out and, despite attempts to recover the drug from his urine, the infection returned and he died in March. Despite this tragic outcome, the trial proved penicillin's remarkable efficacy in humans and intensified the urgency to scale up production for wider use.
Location: Oxford, England
US Mass-Production Scale-Up for the War Effort
In mid-1941, Howard Florey and Norman Heatley travelled to the United States to enlist American help in producing penicillin at scale, collaborating with the USDA's Northern Regional Research Laboratory in Peoria, Illinois. Researchers there discovered a far more productive mould strain from a mouldy cantaloupe and developed deep-tank fermentation, which enabled industrial-scale cultivation of the mould. American pharmaceutical companies including Pfizer, Merck, and Squibb ramped up production, and output rose from negligible laboratory quantities to hundreds of millions of units by 1943. This unprecedented industrial mobilisation made penicillin a cornerstone of the Allied war effort and a model for subsequent drug scale-up.
Location: Peoria, Illinois, United States
Streptomycin Discovered — The Golden Age of Antibiotics Begins

In October 1943, Selman Waksman and his PhD student Albert Schatz at Rutgers University isolated streptomycin, the first antibiotic effective against Gram-negative bacteria and the first effective treatment for tuberculosis, one of humanity's greatest killers. Waksman is credited with coining the modern sense of the word "antibiotic," and his laboratory went on to isolate more than a dozen further antibiotics. The success of penicillin and streptomycin opened a golden age of antibiotic discovery lasting from the 1940s into the 1960s, yielding tetracyclines, chloramphenicol, erythromycin, and many other classes that transformed the treatment of bacterial infections worldwide.
Location: New Jersey, United States
D-Day — Penicillin Widely Available for Allied Casualties

By the time of the D-Day landings on 6 June 1944, Allied forces had sufficient penicillin supplies to treat all serious casualties of the Normandy invasion, a milestone in the drug's mass battlefield deployment. Penicillin dramatically reduced deaths from wound infections and sepsis among soldiers, among the leading causes of battlefield mortality in previous conflicts. Its success in treating troops accelerated public demand for civilian access and cemented penicillin's reputation as one of the most consequential medical developments of the 20th century. After the war, penicillin became widely available to the general public, transforming everyday medicine.
Location: Normandy, France
Nobel Prize Awarded to Fleming, Florey, and Chain
The Nobel Assembly at the Karolinska Institute announced on 25 October 1945 that the Nobel Prize in Physiology or Medicine would be awarded jointly to Sir Alexander Fleming, Ernst Boris Chain, and Sir Howard Florey "for the discovery of penicillin and its curative effect in various infectious diseases," with the prize shared equally among the three laureates. The award, presented at the Nobel ceremony in Stockholm on 10 December 1945, recognised both Fleming's foundational discovery and the Oxford team's work to develop penicillin into a usable, mass-producible drug. In his Nobel lecture, Fleming presciently warned that misuse of penicillin could select for resistant bacteria, foreshadowing the resistance crisis to come.
Location: Stockholm, Sweden
Tetracycline Discovered — The First Broad-Spectrum Antibiotic
In 1948, Benjamin Duggar at Pfizer isolated chlortetracycline (Aureomycin) from a soil bacterium found in a Missouri field, marking the discovery of the first broad-spectrum antibiotic effective against a wide range of bacterial infections. Tetracycline-class antibiotics became widely prescribed for conditions ranging from respiratory infections to acne. Their discovery opened a new frontier in antibiotic therapy, as they could target bacteria that penicillin could not reach.
Methicillin and the Rise of Antibiotic-Resistant Bacteria
In 1959, the semi-synthetic penicillin methicillin was introduced to treat infections caused by penicillinase-producing staphylococci. Just two years later in 1961, the first cases of methicillin-resistant Staphylococcus aureus (MRSA) were reported in the United Kingdom. MRSA quickly spread worldwide, becoming a leading cause of hospital-acquired infections and demonstrating that bacteria could evolve resistance even to the newest antibiotics within years of their introduction.
Linezolid Approved — First New Antibiotic Class in 35 Years
In April 2000, the U.S. Food and Drug Administration approved linezolid (marketed as Zyvox), the first member of a new class of antibiotics called oxazolidinones and the first genuinely novel class of antibiotics introduced since the 1960s. Linezolid proved effective against drug-resistant Gram-positive bacteria including MRSA and vancomycin-resistant Enterococci (VRE), offering a critical new weapon for treating hospital-acquired infections. Its approval broke a decades-long drought in antibiotic innovation and highlighted the growing challenge of antimicrobial resistance.
NDM-1 Superbug Gene Identified — Resistance to Last-Resort Antibiotics
In August 2010, an international research team led by Cardiff University published findings in The Lancet identifying the New Delhi metallo-beta-lactamase (NDM-1) gene, which enables bacteria to produce an enzyme that breaks down carbapenem antibiotics — the drugs of last resort for treating resistant infections. First detected in 2008 in a Klebsiella pneumoniae culture from a Swedish patient treated in India, the gene was found on plasmids capable of transferring between bacterial species, raising fears of unstoppable global spread. The report triggered worldwide alarm and cemented NDM-1 as a symbol of the growing antimicrobial resistance crisis.
WHO Declares Antimicrobial Resistance a Global Threat
In April 2014, the World Health Organization released its first global report on antimicrobial resistance, declaring that AMR "is no longer a prediction for the future, it is happening right now in every region of the world and has the potential to affect anyone, of any age, in any country." The report documented widespread resistance to common bacteria, including resistance to last-resort treatments such as carbapenems and fluoroquinolones, and warned that without urgent action the world was heading toward a post-antibiotic era in which common infections and minor injuries could once again kill. The report marked antimicrobial resistance's emergence as a top-tier global public health priority and prompted coordinated international responses.
Location: Geneva, Switzerland
The Ongoing Antimicrobial Resistance Crisis
Antimicrobial resistance is now one of the top global public health threats: WHO estimates that bacterial AMR was directly responsible for 1.27 million deaths and associated with 4.95 million deaths in 2019, with projections of up to 10 million deaths per year by 2050 without coordinated action. Misuse and overuse of antibiotics in human medicine and agriculture, combined with a thin pipeline of new drugs, are accelerating the spread of resistant pathogens, with roughly one in six laboratory-confirmed bacterial infections worldwide resistant to antibiotics in 2023. WHO and its Quadripartite partners coordinate a global One Health response, and the World Health Assembly adopted an updated Global Action Plan on AMR for 2026–2036. The crisis underscores the unfinished arc of the penicillin story: a discovery that transformed medicine now requires renewed innovation and stewardship to preserve its gains.
Location: Global
World Health Assembly Adopts Updated Global Action Plan on Antimicrobial Resistance 2026-2036

On 23 May 2026, Member States at the 79th World Health Assembly in Geneva adopted the updated Global Action Plan on Antimicrobial Resistance (GAP-AMR) for 2026-2036, marking a major milestone in the global response to AMR. The updated plan, developed through a consultative process led by the Quadripartite organizations — FAO, UNEP, WHO, and WOAH — provides a comprehensive One Health framework for coordinated action across human, animal, plant, and environmental health. It builds on the original GAP-AMR adopted in 2015 and delivers on commitments from the 2024 UN General Assembly Political Declaration on AMR, with strengthened emphasis on prevention-first interventions, surveillance, innovation, and sustainable financing.
FDA Approves Zaynich — New Antibiotic for Drug-Resistant Infections

On 29 May 2026, the U.S. Food and Drug Administration approved Zaynich (cefepime and zidebactam), a novel intravenous antibiotic combination developed by Wockhardt for the treatment of complicated urinary tract infections (cUTI), including pyelonephritis, caused by drug-resistant Gram-negative pathogens. The approval was based on the ENHANCE-1 Phase 3 trial, which demonstrated superiority to meropenem at the test-of-cure visit. Zaynich had previously received Qualified Infectious Disease Product (QIDP) designation from the FDA and represented a significant addition to the limited arsenal against carbapenem-resistant Gram-negative infections.
Scientists Revive Vancomycin Against Drug-Resistant Superbugs
On 22 July 2026, researchers at Cold Spring Harbor Laboratory (CSHL) and Scripps Research announced a breakthrough method to restore the effectiveness of vancomycin, a powerful last-resort antibiotic, against drug-resistant Enterococcus faecium (VRE). Instead of creating a new drug, the team paired vancomycin with a small molecule called pghi-4, which inhibits the bacterial enzyme secreted antigen A (SagA) that contributes to vancomycin resistance. Pghi-4 was originally discovered in 2020 in the CSHL Moses laboratory using a technique called diversity oriented clicking. The combination successfully killed drug-resistant bacteria in both laboratory cultures and mouse models, demonstrating that antibiotic adjuvants can rescue failing medicines.
AI-Designed Bacteriophages Target Drug-Resistant Bacteria

Stanford University researchers used the generative AI model Evo 2 to design novel bacteriophage genomes capable of killing drug-resistant Escherichia coli. Given only a short DNA seed from bacteriophage PhiX174, Evo 2 generated thousands of candidate genome sequences. The team synthesized nearly 300 of these and, after laboratory testing, identified 16 phages with potent E. coli-killing activity. Several AI-designed phages surpassed the killing power of the native virus. A cocktail of all 16 phages rapidly overcame resistance in E. coli strains that had evolved immunity to the natural PhiX174 phage, demonstrating a potential pathway to resistance-resistant antibiotic therapies. The work, published in Science, represents a proof of concept for AI-guided genome design as a tool against antimicrobial resistance.